| Food Sciences and Clinical Nutrition, ISSN 0000-0000 online, Open Access |
| Article copyright, the authors; Journal compilation copyright, Food Sci Clin Nutr and Elmer Press Inc |
| Journal website https://fscn.elmerpub.com |
Original Article
Volume 1, 2026, e6

Age- and Time-Related Changes in Serum Ferritin Levels in Danish Women: A Population-Based Longitudinal Study of 1,174 Women Over a 10-Year Period: Influence of Nutritional Factors
Nils Thorm Milman 
The Glostrup Population Studies, Rigshospitalet, Glostrup, University of Copenhagen and Department of Clinical Biochemistry, Naestved Hospital, University of Zealand, Naestved, Denmark
Manuscript submitted July 9, 2026, accepted September 11, 2026, published online September 28, 2026
Short title: Longitudinal Study of Serum Ferritin in Danish Women
doi: https://doi.org/10.14740/fscn6
| Abstract | ▴Top |
Background: A well-balanced body iron status is essential for women’s health. This study assessed iron status in Danish women in a longitudinal panel setting.
Methods: The study was part of the WHO DAN-MONICA health survey in Copenhagen 1982–1994, comprising 1,174 healthy women in age groups of 30, 40, 50, and 60 years, being invited for examination three times: at inclusion, and 5 and 10 years after inclusion. Blood samples were analyzed for hemoglobin and serum ferritin as a proxy for body iron reserves.
Results: Ferritin levels increased significantly with age from baseline to the end of the study, concurrently with an increasing prevalence of menopause. From MONICA 1 to the MONICA 10 survey, the frequency of high ferritin values > 200 µg/L increased significantly from 3% to 9% while the frequency of low ferritin values < 30 µg/L decreased significantly from 42% to 24%. There was an overall time-related increase in ferritin levels in 40-, 50-, and 60-year-old women in MONICA 10 compared to women of similar age in MONICA 1. After 65 years of age, there was no further increase in ferritin levels. Blood donors had significantly lower ferritin and hemoglobin and higher prevalence of iron deficiency anemia than non-donors but likewise displayed an increase in ferritin with age and time.
Conclusions: There were no indications that the time-related rise in ferritin during the 10-year period was caused by a higher frequency of inflammatory conditions or increase in body mass index. Even though dietary iron intake in premenopausal women is below recommended intake, an age-related increase in ferritin levels occurs, especially after the last childbirth and the menopause; this may be enhanced by an increased intake of meat and alcohol, especially in elderly women, during the observation period. This study suggests that in a female population, ferritin should be monitored with appropriate intervals in order to evaluate changes in iron status.
Keywords: Blood donor; Ferritins; Hemoglobins; Longitudinal studies; Menopause; Menstruation; Nutrition; Pregnancy; Women
| Introduction | ▴Top |
Iron is an essential mineral required for the synthesis of hemoglobin and numerous iron-containing enzymes [1]. In women of childbearing age, blood and iron losses from menstruation and childbirth can make it difficult to maintain an adequate balance between dietary iron intake, iron absorption, and physiological iron losses, thereby compromising body iron reserves. Insufficient iron uptake leads to iron deficiency with both hematologic and non-hematologic consequences [2], whereas iron overload may cause cellular and organ damage, as observed in genetic hemochromatosis [3, 4].
Since the launching of the biological iron status marker serum ferritin in clinical biochemistry in the 1970s, being introduced in population surveys in Denmark in 1991 [5], there have been population-based studies of iron status in many countries, which have been cross-sectional in design. Subsequently, age-related changes in iron status have been derived by combining cross-sectional studies of different age groups [5–7].
In the present longitudinal study, a female population in age groups of 30 to 60 years has been followed and examined in an unbalanced panel study during a 10-year period. The objective was to establish physiological age level cutoffs for serum ferritin among a longitudinal cohort of ethnic Danish women and to evaluate the overall physiological age-related changes in serum ferritin, as a proxy for iron status. Furthermore, to analyze whether time-related changes had occurred during the 10-year observation period since the abolition of the mandatory food iron fortification in 1987. In addition to discuss the potential causes of time-related changes in ferritin levels, especially dietary factors, and to examine the impact of blood donation on iron status in the female population. In this overall general population study, we have not included analysis of possible confounding factors which may affect ferritin levels, e.g., duration of menstruations, methods of contraception, number of childbirths, alcohol consumption, and tobacco smoking, all of which have been described in previous papers.
| Materials and Methods | ▴Top |
Women
This study was approved by the Ethical Committee in Copenhagen County and conducted in compliance with the ethical standards of the responsible institution on human subjects as well as with the Helsinki Declaration. It constituted the Danish part of the World Health Organization initiated multinational study for the “Monitoring of Trends and Determinants in Cardiovascular Disease” (DAN-MONICA) [8], which was conducted at the Copenhagen County Center for the Prevention of Disease in Glostrup Hospital. Oral and written informed consent was obtained from all participants in each of the three MONICA surveys.
This unbalanced panel study examined the same women at two or three time points over a 12-year period: MONICA 1 in 1982–1984, MONICA 5 in 1988–1989, and MONICA 10 in 1993–1994. Accordingly, women included in MONICA 1 were 5 years older at MONICA 5 and 10 years older at MONICA 10.
The selection of the participants is summarized in Figure 1. In 1982, a sample of 1,804 ethnic, non-pregnant Danish women, in age groups of 30, 40, 50, and 60 years, was drawn from the Census Register and examined in the MONICA 1 iron status survey in 1982–1984 [9]; among these women, 1,174 were randomly selected to participate in the present study. All included women were examined in MONICA 1, and the majority subsequently in MONICA 5 and/or in MONICA 10, i.e., all participants had at least two measurements of serum ferritin. The majority of the women were in good health, and according to their records, at most 2–3% might suffer from diseases (inflammatory disease, kidney disease, liver disease, malignancy) which might cause inappropriate elevation of ferritin levels.
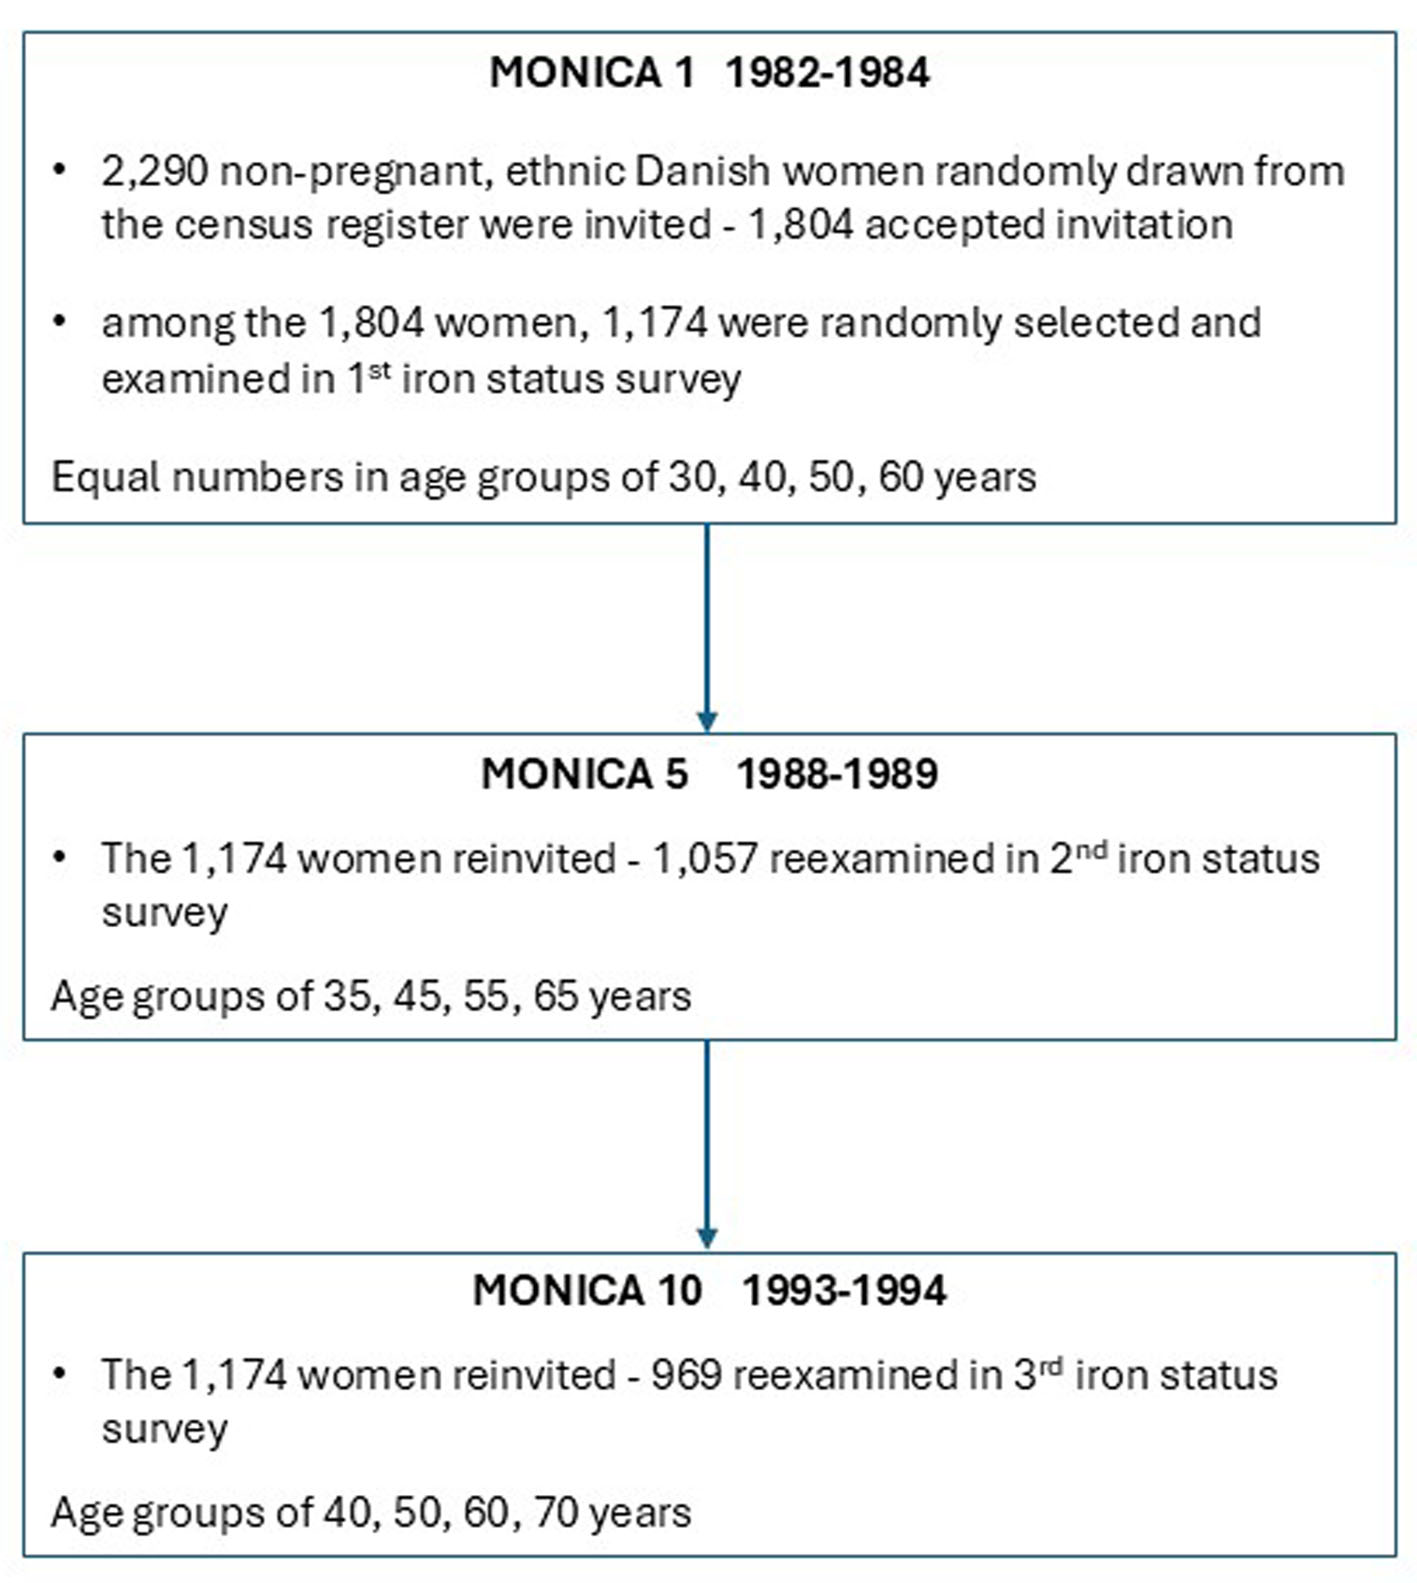 Click for large image | Figure 1. Selection of the female participants in the longitudinal study of serum ferritin in the three MONICA surveys. |
Methods
Participants provided their medical history and blood donor status. Information about menopause was obtained in MONICA 1, and information about age at menarche, duration of menstruations, age at menopause as well as the number of childbirths in MONICA 10 by questionnaires. In this paper, the expression “menopausal” comprises both perimenopausal and postmenopausal women. Body mass index (BMI) was recorded as kg/m2. Dietary habits were assessed in MONICA 1 by 7 days food records. Blood samples were drawn in the fasting state between 08.00 and 11.00 h and serum was immediately separated. In MONICA 1, hemoglobin was analyzed on Coulter Counter Model S Plus and in MONICA 10 on Abbott Cell-Dyn Sapphire Hematology Analyzer. Due to the 10-year time gap between the two surveys, we had no opportunity to compare and standardize the two assays against each other. High and low hemoglobin values were derived from the normal reference interval used in Danish women according to the guidelines from the Danish Society for Clinical Biochemistry, and anemia was defined as hemoglobin values < 120 g/L.
Serum ferritin was analyzed en bloc after the closure of each MONICA survey. In MONICA 1, serum ferritin was measured with an immunoradiometric assay, Phadebas Ferritin PRIST, Pharmacia Diagnostics, Uppsala, Sweden, and in MONICA 5 and MONICA 10 with a radioimmunoassay, Ferritin RIA Amersham. The two assays were compared in a separate study, and Ferritin PRIST values were translated/converted into Ferritin RIA values as previously reported [10]. Besides hemoglobin and ferritin, we did not measure additional iron status markers, e.g., serum transferrin saturation, on a longitudinal basis.
Serum ferritin values < 20 µg/L are indicative of absent stainable bone marrow hemosiderin iron [11]. However, as there is no consensus on which ferritin cutoff level should be employed to be compatible with iron deficiency, we decided to define probable iron deficiency anemia calculated from hemoglobin and ferritin at two ferritin levels: < 30 and < 15 µg/L.
Statistical analysis
Statistical analyses were performed using the Med-Calc statistical software [12]. Due to the non-normal distribution of hemoglobin and ferritin values, they were quoted as medians, interquartile ranges (IQR), and geometric means (antilog of log10 arithmetic mean values). Non-parametric analysis methods included Wilcoxon test (two-tailed) for paired values, Mann–Whitney test (two-tailed) for unpaired values, Friedman test for repeated measures on the same subjects through the three MONICA surveys, Spearman’s rank correlation coefficient rho (rs), chi-square test, Fisher’s exact test, and Kruskal–Wallis test. Parametric analysis was performed using ANOVA F-test. The significance level was set at P < 0.05.
| Results | ▴Top |
Hemoglobin was measured in all women in MONICA 1 and in 969 of them in MONICA 10 as shown in Table 1. Hemoglobin values in MONICA 10 were slightly, but significantly lower compared to MONICA 1. Women in MONICA 1 showed a higher frequency of high values than in MONICA 10, whereas the frequency of low values, i.e., anemia, was similar in both surveys. The frequencies of probable iron deficiency anemia were low in both surveys, being slightly lower in MONICA 10 compared to MONICA 1 (Table 1).
 Click to view | Table 1. Measurements of Blood Hemoglobin in All Women in the MONICA Cohort |
In MONICA 1, blood donors had similar arithmetic mean ± standard deviation (SD) hemoglobin levels, 137 ± 10.3 g/L as non-donors, 139 ± 9.7 g/L (Mann–Whitney test, P = 0.3) and among blood donors, 8/189, i.e., 4.2% compared to 16/1,250, i.e., 1.3% of non-donors, had probable iron deficiency anemia, i.e., hemoglobin < 120 g/L and ferritin < 15 µg/L (Fisher’s exact test, P = 0.009).
In MONICA 10, blood donors had significantly lower hemoglobin, 135 ± 9.3 g/L compared to non-donors, 137 ± 9.7 g/L (Mann–Whitney test, P = 0.02) and among blood donors, 5/109, i.e., 4.6% compared to 11/1,209, i.e., 0.9% of non-donors, had probable iron deficiency anemia (Fisher’s exact test, P = 0.007).
We found a significant positive correlation between ferritin and hemoglobin in non-blood-donors both in MONICA 1 and MONICA 10 (rs = 0.23, P < 0.0001), as well as in blood donors in MONICA 1 (rs = 0.30, P = 0.0001).
Table 2 shows the serum ferritin results in the entire series. There was a significant, gradual increase in ferritin levels over time in the three MONICA surveys; the frequency of high ferritin values > 200 µg/L, compatible with abundant iron reserves or iron overload increased significantly and accordingly, the frequency of low ferritin values < 30 µg/L, compatible with small or absent body iron reserves, decreased significantly. In MONICA 1, among 30- and 40-year-old women, 297/758 (39.2%) had ferritin values < 30 µg/L. Likewise, as the women became 10 years older during the study, the number of menopausal women increased significantly during the observation period, from 38% in MONICA 1 to 57% in MONICA 2.
Click to view | Table 2. Longitudinal Measurements of Serum Ferritin in All Women in the MONICA Cohort |
Menstruation and childbirths
These data were obtained by a questionnaire in the MONICA 10 survey when the women were 40 to 70 years old. Among the 917 responding women, median age at menarche was 14 years (2.5–97.5 percentiles: 11–17 years). Among the 432 responding women, the median duration of menstruation was 5 days (2.5–97.5 percentiles: 3–9 days) and among the 510 responding women, menopause occurred at a median age of 49 years (2.5–97.5 percentiles: 31–56 years).
In response to the question, “Have you ever given birth?”, 824 of the 847 responding women (97.3%) answered “yes”; the median age at first pregnancy was 23 years (range 17–33 years), and the median number of childbirths was 2 (range 1–4 births).
There were significant negative correlations between ferritin levels and the duration of menstruations in 40-year-old women both in MONICA 1 (127 women responding) (rs = −0.20, P = 0.03), as well as in MONICA 10 (196 women responding) (rs = −0.19, P = 0.009).
The number of blood donors is shown in Table 3. The women were interviewed about recent blood donation in MONICA 1 and 10 years later in MONICA 10. The number of donors was highest and similar in 30- to 40-year-old women and subsequently decreased with increasing age from MONICA 1 to MONICA 10.
Click to view | Table 3. The Number of Blood Donors in Women According to Age in MONICA 1 and MONICA 10 Surveys |
Table 4 shows the longitudinal serum ferritin values in blood donors. Donors were defined as those women who donated blood at inclusion in MONICA 1, i.e., they were also classified as donors in the MONICA 5 and MONICA 10 surveys. A few women in the MONICA 10 group were non-donors in MONICA 1but became donors in MONICA 10 and were included in the MONICA 10 donor group.
Click to view | Table 4. Longitudinal Measurements of Serum Ferritin in Women, Blood Donors, in the MONICA Cohort |
Donors, like non-donors, showed a gradual increase in ferritin levels over time (Tables 4 and 5) and the frequency of high ferritin levels did not differ significantly between donors and non-donors (Fisher’s exact test, P = 0.3) (Tables 4 and 5). However, donors had a markedly higher frequency of low ferritin values, indicating low or absent body iron reserves. Specifically, the frequencies of ferritin values < 30 and < 15 µg/L were significantly higher in donors than in non-donors (Fisher’s exact test, P = 0.003 and P < 0.0001, respectively).
Click to view | Table 5. Longitudinal Measurements of Serum Ferritin in Women, Non-Blood-Donors, in the MONICA Cohort |
In MONICA 1, 72% of donors were premenopausal compared to 56% in MONICA 10 (Fisher’s exact test, P = 0.004).
The longitudinal ferritin values in non-blood-donors are shown in Table 5. Ferritin levels increased significantly with age and time just like the frequency of high ferritin values > 200 µg/L, rising from 3.2% in MONICA 1 to 9.2% in MONICA 10. Accordingly, the frequency of low ferritin values < 30 and < 15 µg/L decreased significantly from MONICA 1 through MONICA 5 and MONICA 10.
Table 6 shows the results of the panel study, i.e., ferritin values in the same women are monitored two or three times during the 10-year period.
Click to view | Table 6. Longitudinal Measurements of Serum Ferritin in Women, Non-Blood-Donors, in the MONICA Cohort, Arranged According to Age at Inclusion in MONICA 1 |
From a cross-sectional point of view, with increasing age at inclusion in MONICA 1, we found a significant increase in ferritin levels between the various age groups, except between 30- and 40-year-old women (Table 6 read vertically).
The same pattern was present in MONICA 5, where ferritin values were similar in 35- and 45-year-old women, but significantly higher in 55- and 65-year-old women. MONICA 10 likewise displayed increasing ferritin levels from 40 to 60 years of age, but 60- and 70-year-old women had similar ferritin levels, indicating that the age-related increase in ferritin fades out between 60 to 70 years of age. Concurrently, in both the MONICA 1 and MONICA 10 surveys, the percentage of menopausal women increased significantly with age (Table 6 read vertically).
In the panel study (Table 6 read horizontally), we observed a significant increase in ferritin levels over time in 30-, 40-, and 50-year-old women from MONICA 1 through MONICA 5 to MONIСA 10, ехсеpt between 35- and 40-year-old women in MONICA 5 vs. MONICA 10. Sixty-year-old women displayed a slight increase in ferritin until 65 years of age, and hereafter ferritin levels remained stable, and no further increase was observed at 70 years of age. From MONICA 1 to MONICA 10, the percentage of menopausal women increased significantly with age in 30-, 40-, and 50-year-old women (Table 6 read horizontally).
In Table 7 we compared ferritin levels in women of the similar age in MONICA 1 and in MONICA 10. In 40-year-old women, ferritin levels were slightly higher in 1994 compared to 1984, but the difference was not statistically significant, while 50- and 60-year-old women had significantly higher ferritin values in 1994 compared to 1984.
Click to view | Table 7. Serum Ferritin in Women, Non-Blood-Donors of Similar Age in the MONICA 1 and MONICA 10 Surveys |
Furthermore, we assessed the relationship between BMI and serum ferritin in non-blood-donors as shown in Table 8. Overall, BMI levels were quite stable during the 10-year observation period. We observed a slight increase from 30 to 60 years of age after which BMI levels stabilized. In general, there were no clinically relevant correlations between BMI and ferritin levels, not even in overweight women with BMI ≥ 25 kg/m2.
Click to view | Table 8. Correlations Between Body Mass Index and Serum Ferritin in Women, Non-Blood-Donors, in the MONICA Cohort |
| Discussion | ▴Top |
This study evaluates serum ferritin levels as a substitute for body iron reserves in a 10-year longitudinal setting in apparently healthy ethnic Danish women. The aim of our previous cohort study was to evaluate the effect of the abolition of the mandatory food iron fortification in Denmark running from 1954 to 1987 [9]. This study also differs from the cohort study [9] by the inclusion of the serum ferritin results from the MONICA 5 survey and by reporting the results in an individual setup as panel study.
During the observation period, hemoglobin levels were by and large unchanged, although slightly different. This could in part be due to the use of two different analysis methods, and partly due to the large numbers of participants, making even small differences significant. However, the prevalence of low hemoglobin values was similar in MONICA 1 and MONICA 10, but the prevalence of possible iron deficiency anemia was lower in MONICA 10 compared to MONICA 1; this may be elicited by the higher prevalence of menopausal women and a lower prevalence of blood donors in MONICA 10 compared to MONICA 1.
We observed a similar slight difference between hemoglobin values in men in the MONICA 1 and MONICA 10 surveys [13], supporting the concept that the two different hemoglobin assays were mainly responsible for the differences in hemoglobin values. However, we consider the slight difference in hemoglobin levels to be of no clinical importance.
Concerning the two serum ferritin assays, we rely on that the levels are comparable, based on our previous study comparing the results of the two methods in order to convert values from one assay to the other [10]. In all three surveys, serum ferritin was analyzed en bloc after the survey had been closed and with these assays, we had no reason to believe that the one-time freezing, storage, and thawing process should have any significant influence on ferritin levels.
We included blood-donor data in this population-based survey because blood donation is the community-initiated activity with the greatest impact on body iron status, lowering ferritin levels across all age groups (Tables 3 and 4). Consequently, in both MONICA 1 and MONICA 10, low ferritin values < 30 and < 15 µg/L were significantly more common in donors than in non-donors (Tables 4 and 5), and possible iron deficiency anemia was also significantly more prevalent among donors.
During the observation period, the donation frequency decreased significantly with age in women being 40, 50, and 60 years old at inclusion, which in part may counteract the decline in ferritin in the entire series. This was a consequence of the general drop in blood donation rates in Greater Copenhagen during the observed decade [14]. Also, it is not appropriate that the prevalence of premenopausal women (having a lower iron status than menopausal women) in the donor group is significantly higher than in the non-donor group. Clearly, body iron status in most women of childbearing age is not designed to tolerate the iron losses induced by blood donation unless careful monitoring of serum ferritin and appropriate iron supplementation is administered [15].
The principal observations of this study were the high prevalence of low serum ferritin values < 30 µg/L indicating low or absent iron reserves (Table 2) and the significant gradual increase in ferritin levels and high ferritin values with age in women being 30, 40, and 50 years old at inclusion in MONICA 1, while ferritin in 60-year-old women increased slightly to 65 years of age where it reached a stable level (Table 6 read horizontally). These results are in accordance with those of the cross-sectional study by Barton et al [7] in American women. This increase was observed in both blood donors and non-donors.
Thus, the age-related increase in ferritin values to a stable level around 60 to 65 years of age, i.e., 11–15 years after the menopause, appears to be the “normal” physiologic pattern in women. Previous studies have shown that ferritin levels in Danish women display a gradual but slight increase from 15–16 to 30 years of age [6, 16] and the outcome of the present study demonstrates that the increase in ferritin is a process which continues until late middle age (Table 5).
The major cause for the age-related increase in ferritin in the MONICA cohort appears to be the rising prevalence of menopausal women during the 10-year observation period, increasing from 38% in MONICA 1 to 57% in MONICA 10.
In addition to the age-related changes in ferritin, we discovered time-related changes; in 1994, women aged 50 and 60 years of whom the majority were menopausal had higher ferritin levels than women of similar age in 1984 (Table 7), indicating a general, age-independent, time-related rise in ferritin levels during this period; this rise was also observed in premenopausal 40-year-old women, but did not reach the level of significance.
In women of childbearing age, body iron status is strongly dependent on the delicate balance between iron losses by menstruations and childbirths on the one side and food iron intake and iron absorption on the other side. In this study, the menarche started at median 14 years of age and menstruations continued until median 49 years of age, i.e., most women had monthly blood losses for a median of 35 years. Accordingly, a significant negative correlation existed between ferritin and the duration of menstruation as previously described [17, 18].
Prior to the inclusion in MONICA 1, nearly all women had given birth to two children, which contributes to depletion of iron reserves [9]. Before and during the study period, there were no recommendations concerning iron supplementation during pregnancy. However, as a consequence of our earlier research comparing the iron status of pregnant women taking placebo vs. those receiving iron [19], the Danish Health Authority has since the early 1990s recommended regular iron supplementation during pregnancy.
Among other factors, iron absorption on the long term depends on the magnitude of body iron reserves. With increasing iron reserves, i.e., increasing ferritin levels, iron absorption declines through the interaction of hepcidin, which is a main regulator of intestinal iron uptake. Hepcidin inhibits iron absorption through inhibition of the iron transporter ferroportin. As body iron reserves rise, hepcidin levels increase as well in order to slow down iron uptake [20, 21].
Besides being a biological marker of body iron status, ferritin is an acute phase reactant, increasing by the presence of infection and/or inflammation [22]. However, we did not include analysis of potential confounders, such as metabolic health, non-adipose-related subclinical inflammation, e.g., with elevated C-reactive protein, which may inappropriately increase ferritin levels, in the analysis.
Because the time-related increase in serum ferritin from 1984 to 1994 was observed in 40-, 50-, and 60-year-old women of similar age (Table 7), it seems unrealistic to assume that the frequency of inflammation, liver, kidney and cancer diseases, all known to be connected with inappropriate elevation of ferritin [4], should be systematically higher in 1994 than in 1984. Therefore, increasing inflammation, etc., is very unlikely to cause the observed increase in ferritin over time.
Adipose tissue can induce metabolic dysfunction and low-grade inflammation [23, 24], explaining why a high BMI can be associated with inflammation and elevated serum ferritin levels being inappropriately high compared to body iron reserves.
The BMI levels showed only moderate age- and time-related differences in the MONICA cohort and the mean BMI in the entire series was not significantly different in the MONICA 1 and MONICA 10 surveys (Table 8). BMI increased slightly with age in both surveys, reaching a maximum around 50 to 60 years of age. Thorough analysis of the association between BMI and serum ferritin levels did not show any consistent clinically relevant covariation (Table 8). Consequently, we have no reason to assume that variations in BMI should contribute to the observed age- and time-related changes in ferritin.
The observed time-related increase in ferritin during the 10-year period in 40-, 50-, and 60-year-old menopausal women seems most likely to be caused by changes in extrinsic lifestyle factors, especially nutritional factors; interestingly, a similar time-related increase in ferritin was observed in the male population of the MONICA cohort [13].
All iron in the human body originates from the absorption of iron in the food and the intestinal uptake depends both on the total amount and chemical composition of iron in the diet and the balance between the content of inhibitors and promoters of iron absorption in the meals [25]. Vegetarians generally have a low iron status [25]; however, there is no information about the frequency of female vegetarians in Denmark in the 1980s and 1990s, but we assume that the number was very low.
Nutrition surveys in Denmark and other European countries consistently show that the majority of women of childbearing age have a dietary iron intake, which is markedly lower than the recommended daily intake (RDI) of 15 mg/day [26]. In the MONICA 1 associated dietary survey, women had an arithmetic mean food iron intake of 11.4 ± 4 mg/day [27]. In 1985, when the collection of data in MONICA 1 was terminated, the first Danish National Nutrition Survey reported a median iron intake in women of 12.4 mg/day [28], which is the highest reported intake in Denmark, probably because the Danish food composition tables were still in the development phase. In 1995, when the MONICA 10 survey was closed, the Danish National Nutrition Survey reported a median iron intake in 25- to 64-year-old women of 9.1 mg/day [29]. These and subsequent surveys have shown that median iron intake in women has been relatively stable over the last 30 years, ranging from 8 to 9 mg/day. In the latest Danish National Nutrition Survey 2021–2024 [30], the median iron intake in 25- to 70-year-old women was 9.6 mg/day and 95% of the women of childbearing age had an intake below RDI, whereas the iron intake in postmenopausal women was adequate, corresponding to the present RDI of 8 mg/day.
Interestingly, although food iron intake in vegetarians is within the same range and in many even higher than in non-vegetarians, vegetarians generally have a low body iron status and many women in childbearing age display iron deficiency and some even iron deficiency anemia requiring iron supplementation [25]. Our findings that ferritin levels in 40-, 50-, and 60-year-old women as well as in men [13] have increased over time despite a relatively unchanged food iron intake and despite the abolition of the ineffective food iron fortification in 1987, suggest that changes in the composition of the food iron and in the balance between inhibitors and promoters of iron absorption may play a significant role [25]. A diet with a low heme iron content and rich in inhibitors of iron absorption, e.g., polyphenols, phytates, etc., will lower absorption, while a diet rich in promoters, e.g., heme iron, meat factors, alcohol, etc., will stimulate absorption [25].
The composition of the diet, i.e., the balance between promoters and inhibitors of food iron absorption, is crucial for body iron balance [31]. In young Danish women, a diet rich in meat, promoting iron absorption, has a positive effect on maintaining body iron reserves, while a vegetable-based diet, inhibiting iron absorption, entails a decrease in iron reserves [32]. Most Danish women consume a varied diet, in which the most important sources of iron are animal foods, i.e., mammal and poultry meat, and to a lesser extent fish. These foods are rich in both the easily absorbed heme iron as well as non-heme iron and furthermore contain potent iron absorption promoters, the so called “meat-factors” [25].
High meat intake, in particular red meat, is positively associated with serum ferritin levels [33]. Due to the increasing prosperity in the population, the intake of red meat in Danes increased steadily from the 1980s to 1999 and subsequently continued to rise slowly, now having reached a stable level [34]. The Danish Nutrition Surveys in 1985 [28] and 1995 [29] showed that the consumption of meat increased during this period. However, in general, women of childbearing age had a relatively low intake of meat, especially of red meat, while the consumption of meat was higher in elderly menopausal women.
In the 2021–2024 Danish National Nutrition Survey, 18- to 80-year-old women had a median meat intake of 644 g/week (compared to 1,057 g/week in men) but still exceeding the present Official Danish Dietary Guidelines of 350 g/week [30]. The latest Official Danish Dietary Guidelines in 2021 advise people to eat less meat and if they have meat, they should preferably eat poultry meat [30].
Despite a high-meat culture, many Danes are now aiming at reducing consumption due to climate and health concerns, as well as rising meat prices, with young people and women leading this shift.
Alcohol consumption in Denmark is among the highest compared to other European countries and consumption has increased steadily from 1985 to 2001, especially in elderly women [35]. Alcohol intake is clearly positively correlated to ferritin levels [36] because it is a significant promoter of intestinal iron uptake in two aspects. Pure alcohol has a moderate stimulating effect on gastric acid production, but drinks like beer, wine, and cocktails can enhance iron absorption by increasing gastric acid output [37]. However, the most important promoting influence on iron uptake is probably exerted through the alcohol-induced downregulation of hepcidin production in the liver [21, 38] allowing more food iron to be absorbed.
Dietary surveys tend to underestimate individual alcohol consumption. In this 10-year-long study period, alcohol intake was unchanged in premenopausal women but increased significantly in menopausal women [9]. This may partially explain our finding that 40-, 50-, and 60-year-old women had higher ferritin in 1994 compared to women of similar age in 1984 (Table 7). Alcohol consumption was positively correlated to serum ferritin levels in women in the MONICA 10 survey [39]. In the latest Danish Nutrition Survey [30], 25- to 70-year-old women stated to have an alcohol consumption of 4 g/day (28 g/week) which is well below the maximum recommended intake of 120 g/week [40], probably due to underreporting.
The age-related increase in ferritin levels in 40- to 60-year-old women is most likely due to physiological mechanisms, i.e., an increased fraction of women entering the menopause thus avoiding menstrual iron losses, whereas the time-related increase in ferritin appears to be elicited by nutritional factors, i.e., increased intake of meat and alcohol. Nevertheless, the increase in ferritin levels comes to an end at 60 to 65 years of age after body iron reserves have been replenished and reached a certain level.
In Denmark, the Danish Veterinary, Food, Agriculture and Fisheries Agency monitors the dietary habits in regular National Dietary Surveys, none of which have included assessment of body iron status. The only population-based study of iron status in Danes has been performed in the MONICA cohort [6, 13].
A balanced body iron status (not too much and not too little) is essential for healthy life. The results of this paper show that in general, women of childbearing age have low body iron reserves and furthermore that iron status in the Danish population is not a stable factor but may change due to variations in lifestyle and nutrition. A report from the Danish Veterinary, Food, Agriculture and Fisheries Agency has recommended monitoring serum ferritin levels in the population with appropriate intervals [41], which is especially relevant in women of childbearing age.
Conclusions
Serum ferritin, used as a proxy for body iron reserves, was measured in a longitudinal panel study of 1,174 apparently healthy Danish women aged 30, 40, 50, and 60 years over a 10-year period. Overall, menstruating women of childbearing age had low ferritin levels, with 39% having ferritin < 30 µg/L, consistent with low or absent body iron reserves. Across this cohort, ferritin levels increased significantly with age from baseline to the end of the study, largely reflecting the increasing prevalence of menopause. At the same time, the frequency of high ferritin values > 200 µg/L increased, whereas the frequency of low values < 30 µg/L decreased significantly. Ferritin levels did not increase further after 65 years of age. Blood donors had substantially lower ferritin levels than non-donors in all age groups and a higher prevalence of iron deficiency anemia.
In addition, we observed an overall time-related increase in ferritin levels in 40-, 50-, and 60-year-old women in MONICA 10 compared to women of similar age in MONICA 1. There were no indications that the time-related rise in ferritin during this 10-year period was caused by a higher BMI or an increased prevalence of inflammatory conditions. The time-related increase in ferritin is most likely due to changes in nutritional factors, e.g., an increased intake of meat and alcohol, both of which promote iron absorption. Almost all women of childbearing age had a dietary iron intake which was markedly lower than the RDI, whereas the iron intake in postmenopausal women fulfilled the requirements of the recommended intake. These findings suggest that body iron status (serum ferritin) in a population should be monitored at appropriate intervals. This is especially important in women of childbearing age, having a high frequency of iron depletion and iron deficiency. Please note that the results from this population of ethnic Danish women are country/region-specific and not directly applicable to populations of other ethnicities or regions with different dietary patterns.
Acknowledgments
The author is grateful to Senior Advisor, Cand. Brom. Sisse Fagt, National Food Institute, Technical University of Denmark, Copenhagen, for information about food iron intake in Denmark and to CEO Eskil Krogh and CEO Kristian Krogh, Pharmovital ApS, Rosenkæret 11B, DK-2860 Søborg, Denmark, for helpful assistance.
Financial Disclosure
The study was supported by The Health Insurance Foundation (grant H 11-23-89), The Danish Hospital Foundation for Medical Research, Region of Copenhagen, The Faroe Islands and Greenland (Grant 46-83), The Research Foundation of the Danish Voluntary Blood Donors, and the Danish Health Authority. The funding sources were not involved in the study design, data collection, analysis and interpretation, manuscript writing, or the decision to submit the article for publication.
Conflict of Interest
The author declares to have no conflict of interest.
Informed Consent
All participants presented informed consent to participate in the study.
Author Contributions
NTM provided blood samples and performed the analyses of hemoglobin and serum ferritin in the population study. Statistical analyses were performed by NTM and the manuscript was written by NTM.
Data Availability
The data supporting the findings of this study are available from the corresponding author upon reasonable request.
Abbreviations
BMI: body mass index; IQR: interquartile range; SD: standard deviation
| References | ▴Top |
- Ganz T. Systemic iron metabolism. Adv Exp Med Biol. 2025;1480:33-45.
doi pubmed - Auerbach M, DeLoughery TG, Tirnauer JS. Iron deficiency in adults: a review. JAMA. 2025;333(20):1813-1823.
doi pubmed - Milman N, Pedersen P, a Steig T, Byg KE, Graudal N, Fenger K. Clinically overt hereditary hemochromatosis in Denmark 1948-1985: epidemiology, factors of significance for long-term survival, and causes of death in 179 patients. Ann Hematol. 2001;80(12):737-744.
doi pubmed - Girelli D, Marchi G, Busti F. Diagnosis and management of hereditary hemochromatosis: lifestyle modification, phlebotomy, and blood donation. Hematology Am Soc Hematol Educ Program. 2024;2024(1):434-442.
doi pubmed - Milman N, Kirchhoff M. Iron stores in 1359, 30- to 60-year-old Danish women: evaluation by serum ferritin and hemoglobin. Ann Hematol. 1992;64(1):22-27.
doi pubmed - Milman N. Serum ferritin in Danes: studies of iron status from infancy to old age, during blood donation and pregnancy. Int J Hematol. 1996;63(2):103-135.
doi pubmed - Barton JC, Acton RT, Dawkins FW, Adams PC, Lovato L, Leiendecker-Foster C, McLaren CE, et al. Initial screening transferrin saturation values, serum ferritin concentrations, and HFE genotypes in whites and blacks in the Hemochromatosis and Iron Overload Screening Study. Genet Test. 2005;9(3):231-241.
doi pubmed - Bothig S. WHO MONICA Project: objectives and design. Int J Epidemiol. 1989;18(3 Suppl 1):S29-37.
pubmed - Milman N, Byg KE, Ovesen L, Kirchhoff M, Jurgensen KS. Iron status in Danish women, 1984-1994: a cohort comparison of changes in iron stores and the prevalence of iron deficiency and iron overload. Eur J Haematol. 2003;71(1):51-61.
doi pubmed - Milman N, Bentzon MW, Graudal N, Juul-Jorgensen B. Statistical pitfalls in the comparison between two commercial serum ferritin kits, Pharmacia and Amersham. Dan Med Bull. 1993;40(4):508-510.
pubmed - Milman N, Pedersen NS, Visfeldt J. Serum ferritin in healthy Danes: relation to marrow haemosiderin iron stores. Dan Med Bull. 1983;30(2):115-120.
pubmed - MedCalc® Statistical Software version 23.5.2 MedCalc Software Ltd, Ostend, Belgium; https://www.medcalc.org; 2026.
- Milman NT. Age- and time-related changes in serum ferritin in Danish men: a population-based longitudinal study of 1,199 men over a 10-year period; influence of nutritional factors. Food Sci Clin Nutr. 2026;1:e4.
- https://bloddonor.dk/ Accessed 08.07.2026.
- Milman N, Sondergaard M, Sorensen CM. Iron stores in female blood donors evaluated by serum ferritin. Blut. 1985;51(5):337-345.
doi pubmed - Milman N, Backer V, Laursen EM, Graudal N, Ibsen KK, Jordal R. Serum ferritin in children and adolescents. Results from population surveys in 1979 and 1986 comprising 1312 individuals. Eur J Haematol. 1994;53(1):16-20.
doi pubmed - Milman N, Kirchhoff M, Jorgensen T. Iron status markers, serum ferritin and hemoglobin in 1359 Danish women in relation to menstruation, hormonal contraception, parity, and postmenopausal hormone treatment. Ann Hematol. 1992;65(2):96-102.
doi pubmed - Milman N, Rosdahl N, Lyhne N, Jorgensen T, Graudal N. Iron status in Danish women aged 35-65 years. Relation to menstruation and method of contraception. Acta Obstet Gynecol Scand. 1993;72(8):601-605.
doi pubmed - Milman N, Agger AO, Nielsen OJ. Iron supplementation during pregnancy. Effect on iron status markers, serum erythropoietin and human placental lactogen. A placebo controlled study in 207 Danish women. Dan Med Bull. 1991;38(6):471-476.
pubmed - Collins JF, Wessling-Resnick M, Knutson MD. Hepcidin regulation of iron transport. J Nutr. 2008;138(11):2284-2288.
doi pubmed - Harrison-Findik DD. Is the iron regulatory hormone hepcidin a risk factor for alcoholic liver disease? World J Gastroenterol. 2009;15(10):1186-1193.
doi pubmed - Kernan KF, Carcillo JA. Hyperferritinemia and inflammation. Int Immunol. 2017;29(9):401-409.
doi pubmed - Kawai T, Autieri MV, Scalia R. Adipose tissue inflammation and metabolic dysfunction in obesity. Am J Physiol Cell Physiol. 2021;320(3):C375-C391.
doi pubmed - Han H, Ni P, Zhang S, Ji X, Zhu M, Ma W, Ge H, et al. The association of body mass index and weight waist adjustment index with serum ferritin in a national study of US adults. Eur J Med Res. 2023;28(1):374.
doi pubmed - Milman NT. A review of nutrients and compounds, which promote or inhibit intestinal iron absorption: making a platform for dietary measures that can reduce iron uptake in patients with genetic haemochromatosis. J Nutr Metab. 2020;2020:7373498.
doi pubmed - Milman NT. Dietary Iron Intake in Women of Reproductive Age in Europe: A Review of 49 Studies from 29 Countries in the Period 1993-2015. J Nutr Metab. 2019;2019:7631306.
doi pubmed - Jorgensen LM, Kirchhoff M, Schultz-Larsen K, Schroll M. Food and nutrient intake in Denmark estimated by 7-days food records. III. Intake of vitamins, minerals and trace elements. Scand J Nutr. 1992:36:8-11.
- Haraldsdottir J, Holm L, Jensen JH, Moeller A. Dietary habits in Denmark 1985. Who eats what? (in Danish). Copenhagen: National Food Agency of Denmark. Publication no. 154. 1987.
- Andersen NL, Fagt S, Groth MV, et al. Dietary habits in Denmark 1995. Main results (in Danish). Copenhagen: National Food Agency of Denmark. Publication no. 235, 1995.
- Fagt S, Christensen T, Biltoft-Jensen A, Matthiessen J, Christensen C, Soerensen MR, Henriksen K, et al. Dietary habits in Danes 2021-2024. Main results. (in Danish). DTU Fodevareinstituttet. 2026. ISBN: 978-87-7586-069-2.
- Milman NT. Managing genetic hemochromatosis: an overview of dietary measures, which may reduce intestinal iron absorption in persons with iron overload. Gastroenterology Res. 2021;14(2):66-80.
doi pubmed - Tetens I, Bendtsen KM, Henriksen M, Ersboll AK, Milman N. The impact of a meat- versus a vegetable-based diet on iron status in women of childbearing age with small iron stores. Eur J Nutr. 2007;46(8):439-445.
doi pubmed - Avila F, Echeverria G, Perez D, Martinez C, Strobel P, Castillo O, Villaroel L, et al. Serum ferritin is associated with metabolic syndrome and red meat consumption. Oxid Med Cell Longev. 2015;2015:769739.
doi pubmed - Fagt S, Trolle E. Forsyningen af fødevarer 1955-1999. Udviklingen af danskernes kost - forbrug, indkoeb og vaner (in Danish). Fodevaredirektoratet. Foedevarerapport. 2001:10. ISBN: 87-90978-72-2.
- Fagt S, Matthiessen F, Biltoft-Jensen A, Groth MV, Christensen T, Hinsch H-J, Hartkopp H, et al. Udviklingen i danskernes kost 1985-2001 med fokus pa sukker og alkohol samt motivation og barrierer for sund livsstil (in Danish). Danmarks Foedevare- og Veterinaerforskning. 2004. ISBN: 87-988242-7-9.
- Milman N, Byg KE, Ovesen L, Kirchhoff M, Jurgensen KS. Iron status in Danish men 1984-94: a cohort comparison of changes in iron stores and the prevalence of iron deficiency and iron overload. Eur J Haematol. 2002;68(6):332-340.
doi pubmed - Chari S, Teyssen S, Singer MV. Alcohol and gastric acid secretion in humans. Gut. 1993;34(6):843-847.
doi pubmed - Ohtake T, Saito H, Hosoki Y, Inoue M, Miyoshi S, Suzuki Y, Fujimoto Y, et al. Hepcidin is down-regulated in alcohol loading. Alcohol Clin Exp Res. 2007;31(1 Suppl):S2-8.
doi pubmed - Milman N, Byg KE, Ovesen L. Iron status in Danes 1994. II: Prevalence of iron deficiency and iron overload in 1319 Danish women aged 40-70 years. Influence of blood donation, alcohol intake and iron supplementation. Ann Hematol. 2000;79(11):612-621.
doi pubmed - https://www.sst.dk/vidensbase/forebyggelse/alkohol/anbefalinger-om-alkohol, accessed 10.09.2026.
- Ovesen L, Astrup A, Hansen M, Koch B, Mejborn H, Michaelsen KF, Milman N, et al. Iron - should the supply in the Danish population be improved? (in Danish: Jern - bor forsyningen i den danske befolkning forbedres?) Danish Veterinary, Food, Agriculture and Fisheries Agency. Fodevarerapport. 2002:18. ISBN: 87-91189-52-7.
This article is distributed under the terms of the Creative Commons Attribution 4.0 International License (CC BY 4.0), which permits unrestricted use, distribution, and reproduction in any medium, including commercial use, provided the original work is properly cited.
Food Sciences and Clinical Nutrition is published by Elmer Press Inc.